Adrenergic modulators change activity of some or all of the α- or ß- adrenergic receptors. There are 5 total subtypes of adrenergic receptors. The α class mainly contract smooth muscles in the body to heighten blood pressure. The ß class increases heart pumping and relaxes the bronchi for more air intake.
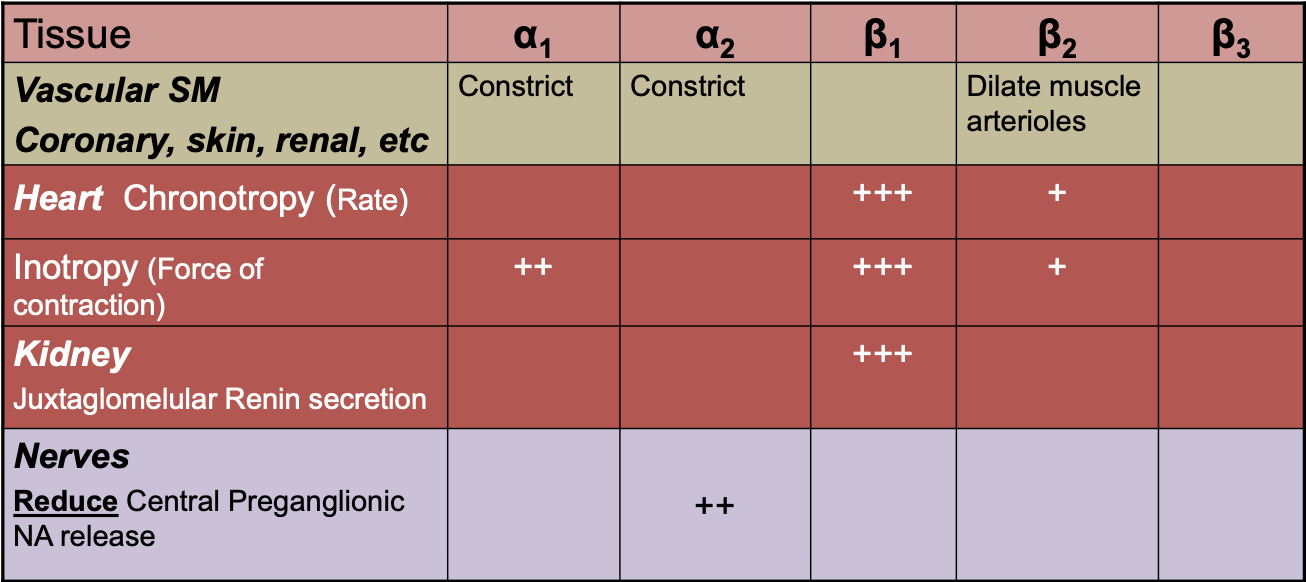
Drug examples
alpha 1 blockers (-zosin)
- Doxazosin (often used with other drugs)
alpha 2 blockers
Beta blockers (b1 for cardio selectivity) -olol
- Metoprolol
- atenolol
- propranolol
- Carvedilol
Beta blockers
These block the ß-adrenergic receptors. The different drugs and generations of drugs have different actions and different properties.
Metoprolol and propranolol are inverse agonists, and they dont not only block receptor activation but decrease baseline effects

Uses
- cardiac rate control: antiarrhythmia used in atrial fibrillation
- angina and MI: makes hearts job easier
- Heart failure: use of carvedilol as vasodilating sympatholytic
- Hypertension (not generally used) used in conditions where SNS is overacting (most HTN patients suffer from atherosclerosis)
- Sometimes:
- Glaucoma: timolol in eye drops for decreases intraocular pressure
- Anxiety: for tremors and increased HR
Why aren’t Beta-blockers mainly used in HTN
1st and 2nd gen beta blockers reduce BP through -ve chronotropic and inotropic effects without vasodilation (while still negatively effecting lipid profiles)
3rd gen ß-blockers also have vasodilator capabilities without major adverse effects
Side effects
- Bronchospasm due to b2 interaction
- Decreases CO can promote heart failure
- Reduced exercise tolerance
- peripheral vasoconstriction
- worsening heart block
- CNS effects (nightmares)
- Worse lipid profiles
- inhibit b2 stimulation of vascular lipoprotein lipase
- increase vldl to HDL levels
- also blunt catecholamine induced glycogenolysis in response to hypoglycaemia
3rd gen also vasodilates which more helpful and have less effects on HR, lipid profiles etc
Doesnt belong dont know what to do with it
atenolol hydrophilicity
lack of hepatic first pass
longer half life
low CNS penetration
metoprolol and carvedilol lipophilic
improved oral absportion
hepatic metabolisn
greater first pass
howerer half life
larger vol of dist resulting in ADR
higher cns penetration
lipophilic drugs often vary in half life due to polymorphismns is cyp2d6
administration
oral admin:metoprolol, c
arvedilol, atenolol, propranolol. Taken with food to slow
down absorption
tartarate immediate release succinate extended release
rapid admin (IV) esmolol, labetalol. emergency and short acting
titrate dose up gradually
withdraw slowly to avoid rebound effects
Pharmacodynamics
snp in ADRb1 gene leads to gly -> arg and leads to increases inherent receptor sensitivbity to b blockers
also ser to gly results in smaller amount of b receptors and loss of response to b blockers
genetic variations in gene encoding CYp2d6
lbroad spectrum
ultrarapid response and low response